



Cemento-Osseous Dysplasia
Cemento-osseous dysplasia (COD) is a benign fibro-osseous condition in which fibrous tissue and cementum-like deposits replace normal bone in tooth-bearing areas.1 Most frequently encountered in middle-age women of African descent, the condition likely arises from mesenchymal cells within the periodontal ligament (PDL).1 The altered bone metabolism can complicate orthodontic treatment, particularly when extractions or implants are involved.
This article continues our series on orofacial pathologies,2,3 documenting the case of an adult patient who was diagnosed with COD in the mandible.
Case Report
A 53-year-old female of African descent presented with the chief concern of crowding in her lower jaw. Clinical examination found extensive restorations, including a lower right second molar implant and an upper right central incisor root canal and crown. Panoramic radiographs provided by the referring dentist showed indistinct radiolucencies in the lower left mandible.
Cone-beam computed tomography revealed an irregular, mixed radiolucent-radiopaque lesion extending from the distal side of the lower left lateral incisor to the mesial side of the lower left first molar, apical to the associated teeth (Fig. 1). The lesion had a radiolucent border with a sclerotic rim, and a radiopaque center. It had expanded the buccal cortical plate without causing displacement or root resorption of the adjacent teeth, which remained vital.
Similar articles from the archive:
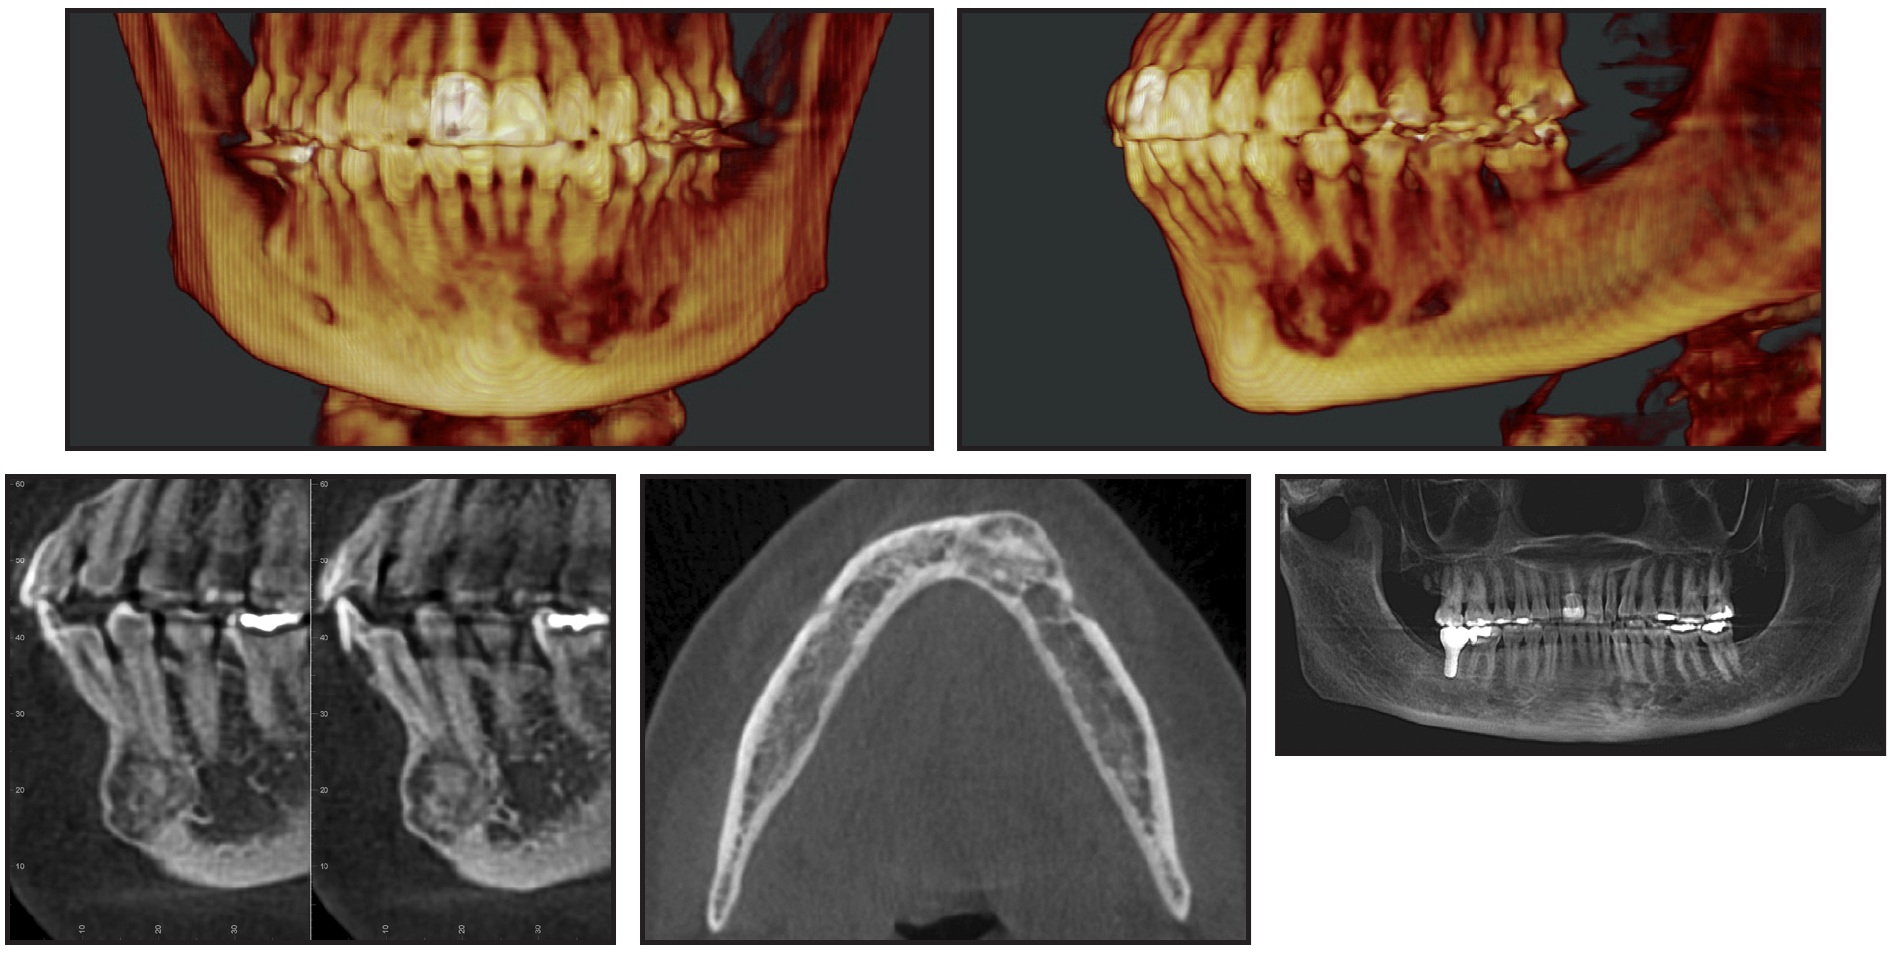
Fig. 1 Cone-beam computed tomography reconstruction of 53-year-old female patient with cemento-osseous dysplasia of anterior mandible, showing mixed radiopaque-radiolucent lesion extending from distal side of lower left lateral incisor to mesial side of lower left first molar, expanding buccal cortical plate.
COD was diagnosed, based on its characteristic radiographic and clinical features. A biopsy was not performed, since the compromised vascularity and altered bone metabolism associated with the condition increased the risk of secondary infection.4
The patient had remained asymptomatic and was unaware of the lesion. She was informed of the diagnosis, disease mechanism, and orthodontic implications. Because the lesion was localized and limited tooth movement would be performed in the affected area, the planned orthodontic treatment began once the patient provided consent.
Discussion
COD is a jaw-specific bone dysplasia that typically presents between the fourth and sixth decades of life, occurring nine times more frequently in women than in men. The bone in the affected area, rather than undergoing normal remodeling, is replaced by fibrous connective tissue that gradually mineralizes. Although the specific cause of COD remains unknown, a possible contributor to its onset and progression is an alteration in cellular signaling, which can lead mesenchymal cells in the apical PDL to differentiate and proliferate abnormally.5
COD lesions are most often located in the anterior mandible, particularly in tooth-bearing regions near the lower incisors and canines, and tend to be localized, although they can also present bilaterally and encompass the posterior mandible or even the maxilla.1,6,7 Teeth adjacent to the lesion remain vital, and patients do not typically report pain or sensitivity in the area. As a consequence, most cases are discovered in routine dental radiographs.
Radiographically, COD appears as either an irregular or a round-to-oval lesion with a radiolucent border. The border varies in width and is surrounded by a band of sclerotic bone apical to the associated teeth. The internal structure of the lesion changes as it develops. The centers of early-stage lesions are mostly composed of radiolucent fibrous tissue. In the intermediate stage, irregular radiopaque areas form as abnormal calcified tissue replaces the fibrous center. Mature lesions are often entirely radiopaque, surrounded by a thin radiolucent margin. Loss of the lamina dura around affected teeth is common, although the tooth structure is usually preserved. While small lesions are confined, larger lesions can displace the cortical plate, as observed in our patient.
The primary differential diagnosis for early (radiolucent) COD is chronic apical periodontitis, which can be ruled out by confirming tooth vitality. A mature (radiopaque) COD lesion may resemble a cementoblastoma, particularly if it is located near mandibular molars, though cementoblastomas are attached to the root surfaces and tend to be better defined. Differential diagnoses also include odontomas, which can present periapically, but are more often occlusal to associated teeth; idiopathic osteosclerosis, which lacks the radiolucent border; and cemento-ossifying fibromas, which are true fibro-osseous neoplasms requiring surgical removal.6-8
When treating a patient with COD, the clinician must consider both the extent of the lesion and the nature of the planned treatment. In general, involved teeth should not be extracted, since poor vascularity and altered mineralization within the lesion can increase the risk of osteomyelitis.9 To minimize complications, the clinician should be prepared to adjust the treatment plan to avoid extractions and implants in the affected region. In a patient with localized periapical or focal COD, however, orthodontic treatment can generally be performed without complications.10,11
REFERENCES
- 1. Neville, B.W.; Damm, D.D.; Allen, C.M.; and Chi, A.C.: Oral and Maxillofacial Pathology, 4th ed., Elsevier Health Sciences, Philadelphia, 2015.
- 2. Jayaraman, S.; Noble, J.; and Kravitz, N.D.: Numb chin syndrome, J. Clin. Orthod. 57:760-762, 2023.
- 3. Kravitz, N.D.; Noble, J.; and Grimsley, B.R.: Carotid aneurysm associated with likely Ehlers-Danlos syndrome, J. Clin. Orthod. 59:106-108, 2025.
- 4. Olgac, V.; Sinanoglu, A.; Selvi, F.; and Soluk-Tekkesin, M.: A clinicopathologic analysis of 135 cases of cemento-osseous dysplasia: To operate or not to operate? J. Stomatol. Oral Maxillofac. Surg. 122:278-282, 2021.
- 5. Günhan, Ö; Kahraman, D.; and Yalçın, Ü.: The possible pathogenesis of cemento-osseous dysplasia: A case series and discussion, Adv. Oral Maxillofac. Surg. 3:100105, 2021.
- 6. Roghi, M.; Scapparone, C.; Crippa, R.; Silvestrini-Biavati, A.; and Angiero, F.: Periapical cemento-osseous dysplasia: Clinicopathological features, Anticancer Res. 34:2533-2536, 2014.
- 7. Decani, S.; Quatrale, M.; Costa, D.; Moneghini, L.; and Varoni, E.: Florid cemento-osseous dysplasia: A case report and review of literature, Heliyon 10:e33746, 2024.
- 8. Kaur, T.; Dhawan, A.; Bhullar, R.S.; and Gupta, S.: Cemento-ossifying fibroma in maxillofacial region: A series of 16 cases, J. Maxillofac. Oral Surg. 20:240-245, 2021.
- 9. Kato, C.N.A.O.; de Arruda, J.A.A.; Mendes, P.A.; Neiva, I.M.; Abreu, L.G.; Moreno, A.; Silva, T.A.; Souza, L.N.; and Mesquita, R.A.: Infected cemento-osseous dysplasia: Analysis of 66 cases and literature review, Head Neck Pathol. 14:173-182, 2020.
- 10. Consolaro, A.; Paschoal, S.R.B.; Ponce, J.B.; and Miranda, D.A.O.: Florid cemento-osseous dysplasia: A contraindication to orthodontic treatment in compromised areas, Dent. Press J. Orthod. 23:26-34, 2018.
- 11. Minhas, G.; Hodge, T.; and Gill, D.S.: Orthodontic treatment and cemento-osseous dysplasia: A case report, J. Orthod. 35:90-95, 2008.
-
 DR. CRUZ WALMA
-
 DR. KRAVITZ
-
 DR. WEISSHEIMER
-
 DR. AKYALÇIN
Dr. Cruz Walma is an Orthodontic Resident, Dr. Kravitz is an Assistant Professor, Dr. Weissheimer is the Clinic Director, and Dr. Akyalçin is the Head of Orthodontics, Harvard School of Dental Medicine, 188 Longwood Ave., Boston, MA 02115. Dr. Kravitz is also the Editor-in-Chief of the Journal of Clinical Orthodontics and in the private practice of orthodontics in South Riding, VA. E-mail Dr. Cruz Walma at david_cruzwalma@hsdm.harvard.edu.
